

Bringing fluoroscopy into a physician office is mostly a regulatory project rather than a purchasing one. The mini C-arm requirements that set your timeline come from three places, and only one of them is the manufacturer. The federal performance standard is satisfied by the device before it ships. Your state radiation control program registers the machine, decides whether a survey is needed, and schedules the inspections. Your own facility policy decides who is permitted to activate the tube and what protective equipment they wear. Practices that plan around all three usually have a unit imaging patients within a few weeks of delivery. Practices that treat it as an equipment order find out about the state paperwork after the crate is already in the hallway.
This guide walks the mini C-arm requirements in the order a practice actually hits them. It is written for the physician, practice manager, or administrator evaluating whether extremity fluoroscopy belongs in the office, and it sticks to what published regulation and manufacturer documentation actually say.
What Are the Mini C-Arm Requirements Set by Federal Regulation?
Federal rules for fluoroscopic equipment live in 21 CFR 1020.32, the FDA performance standard for fluoroscopic systems. These are manufacturing requirements, so a compliant system already meets them when it arrives. They still matter to a buyer, because they explain why a mini C-arm behaves differently from the full-size unit down the hall.
The most commonly misquoted figure is source-to-skin distance. General guidance says a stationary fluoroscope must limit source-to-skin distance to no less than 38 cm and a mobile or portable unit to no less than 30 cm. Neither number applies to a mini C-arm. The regulation carves out C-arm systems manufactured on or after June 10, 2006 with a maximum source-image receptor distance under 45 cm, and requires those to limit source-to-skin distance to no less than 19 cm. Those systems must be labeled for extremity use only. Where a specific surgical application would be impossible at 19 cm, the standard permits shorter operation, but in no case closer than 10 cm, and the manufacturer must publish precautions for whatever spacing method it provides.
That is why mini C-arms ship with a spacer cone. On the OrthoScan Versa, OrthoScan’s published documentation describes the cone as maintaining the minimum source-to-skin distance required by the standard, removed only for procedures that genuinely call for a shorter distance. If a staff member ever asks why the cone cannot simply be left off for convenience, that is the answer, and it is worth putting in writing before the unit arrives.
The same section caps output. Fluoroscopic equipment may not be operable at any combination of tube potential and current producing an air kerma rate above 88 mGy per minute, the figure that replaced the older 10 R per minute limit, except during image recording or with a high-level control activated. Extremity units run far below that ceiling in practice, but the cap is the reason automatic dose control cannot be overridden indefinitely.
Which Mini C-Arm Requirements Come From Your State?
This is the part that actually consumes calendar time, and it is genuinely different in every state. Radiation-producing machines are regulated at the state level, so the mini C-arm requirements that apply to a practice in Texas are not the ones that apply to a practice in Oregon.
Registration is the universal step. The Texas Department of State Health Services publishes a fee schedule for a new certificate of registration, listing $600 for a radiographic machine, bone densitometer, or cone beam CT used in a medical office. Texas requires biennial fees to keep operating the device and a technical renewal application every eight years, with a reminder letter sent 45 days before expiration. Those figures are specific to Texas and should never be assumed to carry across a state line.
Oregon shows how much further a state can go for fluoroscopy specifically. Under the Oregon Health Authority, a physics survey must be completed annually for each fluoroscopic machine by a licensed health physics company, and the resulting patient entrance dose information must be posted on the machine itself. Oregon also requires a fluoroscopy log for each unit recording date, patient name, exam type, machine settings, operator name, and fluoroscopy on-time, plus an annual benchmark review documenting at least two procedures in each of several categories. Hospitals are inspected annually; medical clinics are inspected every other year.
The practical lesson is not that Oregon is strict. It is that the two states differ on almost every operational detail, so the only reliable source for your obligations is your own state radiation control program, contacted before you sign anything. Ask three specific questions: does this unit require a shielding or physicist survey before clinical use, what is the registration timeline after delivery, and what operator credentials does the state recognize.
Who Is Allowed to Operate the Unit?
Operator eligibility is a state question layered on top of a manufacturer question, and practices routinely underestimate both.
On the state side, Oregon points to a specific administrative rule governing activation of the fluoroscopic tube and maintains a list of approved training programs aimed at non-radiologist practitioners. Other states handle this through general x-ray operator certification, and a few leave more of it to facility policy. A physician who has used a C-arm for years in a hospital may still need a state-recognized credential to activate one in an office they own.
On the manufacturer side, the OrthoScan Mobile DI operator manual is direct about installation: do not attempt to install the device without the assistance of an authorized OrthoScan representative, and that representative provides training to familiarize users with proper operating procedures and techniques. Treat that visit as the anchor of your competency file rather than a delivery formality. Note who attended, what was covered, and who was not there, because the people who miss it are the ones who improvise later.
Protective equipment follows the same pattern. The manual states plainly that the requirement to wear personal protective equipment such as lead aprons and dosimetry badges is governed by individual states and may vary from state to state, and that individual facility policies may be more stringent than state regulations. It directs the reader to consult the state or facility radiation safety officer. In other words, the manufacturer will not tell you whether your staff need badges, and the answer is not the same everywhere.
Is a Mini C-Arm Actually Lower Dose Than a Full-Size Unit?
Sales conversations often treat this as settled. The published literature does not, and a practice writing its radiation safety policy should know that before it drafts one.
In a controlled comparison published in Hand in 2018, Van Rappard and colleagues measured a flat panel mini C-arm against a flat panel standard C-arm using a contrast detail phantom and ionization chambers. Image quality favored the mini unit clearly, with an image quality figure of 30.42 versus 63.40 for the standard C-arm, where a lower figure indicates better quality. Radiation went the other direction. Patient entrance skin dose measured 0.5278 mGy per 30 seconds on the mini C-arm against 0.0490 mGy per 30 seconds on the standard unit, roughly a tenfold difference, and scatter at the two measured positions was about three times higher for the mini system. The authors still recommended the flat panel mini C-arm for hand surgery on the strength of its image quality and practicality.
Read that carefully, because it cuts against the common assumption. A smaller machine is not automatically a lower-dose machine at the patient’s skin. What a mini C-arm reliably reduces is the size of the field and the amount of anatomy in the beam. The dose advantage a practice actually realizes comes from technique: pulsed fluoroscopy rather than continuous, last image hold instead of a second exposure, keeping the anatomy close to the receptor, and short on-time. Those are policy decisions, not properties of the hardware.
Modern units give you the levers. Pulsed fluoroscopy on the OrthoScan Versa runs at 30, 15, 7.5, or 2 pulses per second with a selectable dose filter that lowers dose further for adult and pediatric imaging. Choosing a default pulse rate and writing it into your protocol is one of the highest-value decisions a practice makes in its first month.
What Does the Room Actually Need?
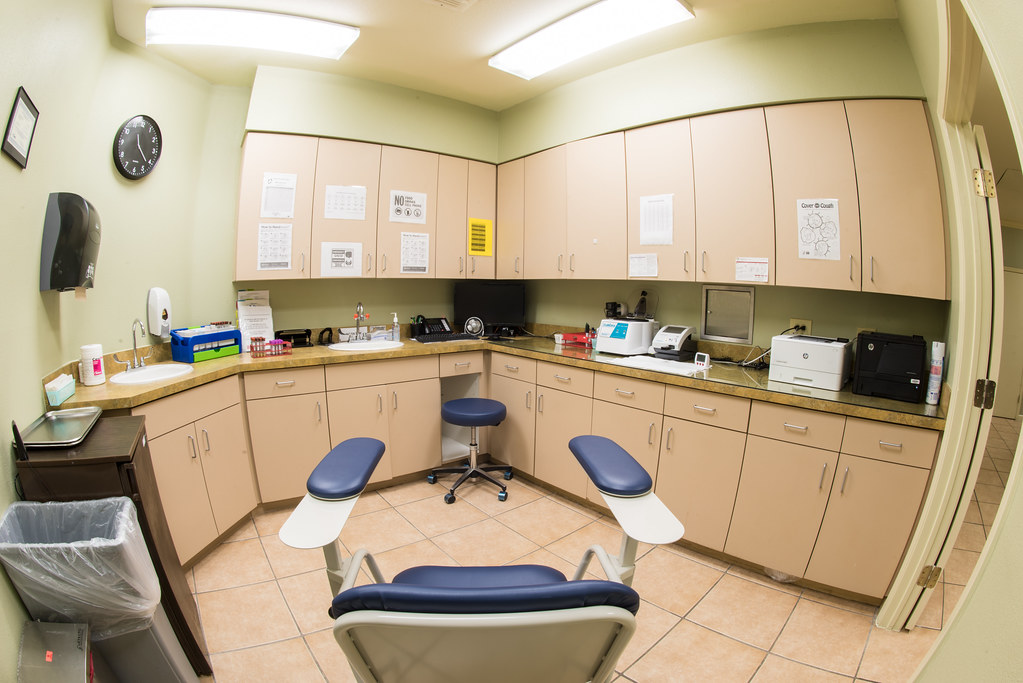
Less than most people expect, which is the whole appeal of the format. Of all the mini C-arm requirements a practice has to satisfy, the physical ones are the easiest.
A mini C-arm is a tabletop instrument. Per OrthoScan’s published Versa specifications, the imaging device weighs 35 pounds, stands 22.3 inches tall, and occupies a footprint of 9.8 by 19.6 inches, so it sits on a desk, a table, or an optional accessory cart and moves between exam rooms instead of anchoring a dedicated imaging bay. Power is ordinary as well: the Mobile DI operator manual states that a special dedicated outlet is not required. Many mini C-arm installations do not need permanent shielding at all, though this is exactly the question to put to your state program rather than to a vendor.
The manual is also clear about the owner’s own duties, and these are the ones that end up in an inspector’s notes. The owner should designate areas suitable for safe operation and service of the device and ensure the device is used only in those designated areas. The owner should ensure user compliance with all applicable local, state, federal, and international laws regarding lead shielding and the use of radiation monitoring devices. Keeping exposures as low as reasonably achievable is stated as the operator’s responsibility. None of that is satisfied by buying the machine; all of it belongs in a written policy.
One detail catches multi-site practices off guard. Moving a unit within your facility is routine and the manual covers it. Moving a unit to a different facility is a separate matter entirely. Under OrthoScan’s warranty terms, the warranty does not apply to a unit moved to a different facility or location by anyone other than OrthoScan or its authorized service personnel, and your state radiation program will normally require notification and a new survey at the new address. If you are contemplating a unit that rotates between two offices, resolve that before purchase, not after.
How Do You Document Dose Once You Are Running?
Current mini C-arms record dose for you, which makes the documentation requirement far less burdensome than practices assume. On the Mobile DI, accumulated dose is displayed in milligray and dose rate in milligray per second, updating in real time during the case, and the dose rate shown is the entrance exposure rate measured at the x-ray window. The dose summary can be reviewed after the case and transferred by DICOM alongside the images.
Where a state requires a fluoroscopy log, as Oregon does, the device output supplies most of the fields and staff supply the rest. Decide early who owns that log and where it lives. A log that exists in principle and nowhere in particular is the most common finding in a first inspection.
7 Steps to Bring Extremity Fluoroscopy In-House
Run these in order. Steps one through three are the ones that move your go-live date.
- Call your state radiation control program first. Confirm registration timeline, fees, whether a survey is required before clinical use, and which operator credentials the state recognizes.
- Confirm the specific unit in writing. Condition, serial number, configuration, and the warranty and service terms that apply to that individual unit.
- Register the machine. File with the state and calendar the renewal and any recurring fee before it slips.
- Schedule any required survey. Where a physics survey applies, book the licensed provider ahead of the first clinical case, not after.
- Designate and document the room. Name the rooms where the unit may be used and record that decision in your radiation safety policy.
- Complete manufacturer training and record it. Attendance, content, and date, filed as the basis of your operator competency records.
- Write the protocol before the first patient. Default pulse rate, protective equipment, dose logging, and who is authorized to activate the tube.
Practices that already run other in-office services will recognize the shape of this. It is the same discipline that governs in-office vascular testing and the same planning that goes into adding PRP to your practice: confirm the rules, document the process, then buy the equipment. Imaging simply has a state agency attached to it.
Frequently Asked Questions
What are the mini C-arm requirements for a physician office?
A physician office generally needs to register the machine with its state radiation control program, satisfy any state requirement for a shielding or physics survey, ensure operators hold whatever credential the state recognizes, provide protective equipment and monitoring as the state requires, designate the rooms where the unit may be used, and maintain the records the state specifies. The device itself already meets the federal performance standard in 21 CFR 1020.32 when it ships.
Do you need a dedicated lead-lined room for a mini C-arm?
Often no. Many mini C-arm installations operate in an ordinary exam room without permanent shielding, because the field is small and the unit is used for extremities. This is a state determination, not a manufacturer one, so confirm it with your state radiation control program or a qualified medical physicist before you plan the space.
How close can the x-ray source get to the patient’s skin?
For C-arm systems made on or after June 10, 2006 with a maximum source-image receptor distance under 45 cm, 21 CFR 1020.32 requires means to limit source-to-skin distance to no less than 19 cm, and those systems must be labeled for extremity use only. Where a specific surgical application requires it, the standard permits operation at a shorter distance but never closer than 10 cm, with manufacturer-published precautions for the spacing method used.
Is a mini C-arm safer than a full-size C-arm?
Not automatically. Van Rappard and colleagues, publishing in Hand in 2018, measured higher patient entrance skin dose and higher scatter from a flat panel mini C-arm than from a flat panel standard C-arm, while finding clearly better image quality from the mini unit. The safety advantage a practice realizes comes from a smaller field and disciplined technique such as pulsed fluoroscopy and short on-time, not from the size of the machine.
Can a mini C-arm move between two office locations?
Moving a unit between rooms in one facility is normal. Moving it to a different facility is not a simple relocation. OrthoScan’s warranty terms exclude a unit moved to a different facility or location by anyone other than OrthoScan or its authorized service personnel, and a state radiation program will normally require notification and a new survey at the new address. Settle a multi-site plan before purchase.
How long does it take to get a mini C-arm running?
The equipment is rarely the constraint. Timelines are usually driven by state registration processing and, where required, scheduling a licensed physics survey. Practices that contact their state radiation control program before ordering typically compress this considerably, because the paperwork runs in parallel with delivery rather than after it.
Where HealthWright Technologies Fits
HealthWright Technologies supplies mini C-arm fluoroscopy systems for physician practices to licensed practices and facilities, and has sold diagnostic and therapeutic equipment to independent physicians since 2000. We quote each system individually, and every quote states the condition, the serial number, and the warranty and service terms that apply to that specific unit in writing before you commit to anything. We supply the equipment; we do not treat patients, and we do not register your machine or write your radiation safety policy for you. The registration, survey, credentialing, and documentation duties described above stay with the practice.
If you are weighing this alongside other in-office services, the planning overlaps with what we have written about ancillary revenue for medical practices, building an in-office diagnostics program, and DME dispensing in the physician office. The regulatory groundwork differs by service, but the sequence does not.
To talk through the mini C-arm requirements that apply where you practice, or to request pricing and availability, contact HealthWright Technologies at contact@healthwrighttechnologies.com or reach us at 60 Bear Creek Marina Road, Mansfield, GA 30055. Call and we will follow up.
This article is general information for licensed healthcare practices and is not legal, regulatory, or clinical advice. Radiation control requirements are set by individual states and change over time; confirm your obligations with your state radiation control program, a qualified medical physicist, or your facility radiation safety officer before acting. Device specifications and labeling are the manufacturer’s and are subject to change; confirm them against the manufacturer’s current documentation for your specific unit. Clinical decisions, including whether imaging is appropriate for a given patient, rest with the treating physician, and patients should consult their healthcare provider about their own care.
Ready to see the CMAT Advantage in your practice?
Book a free 25-minute demo: see the full PAD + autonomic workup and how the three established CPT codes apply, with no obligation. Backed by our 90-day buyback guarantee.
Book a Free Demo →


