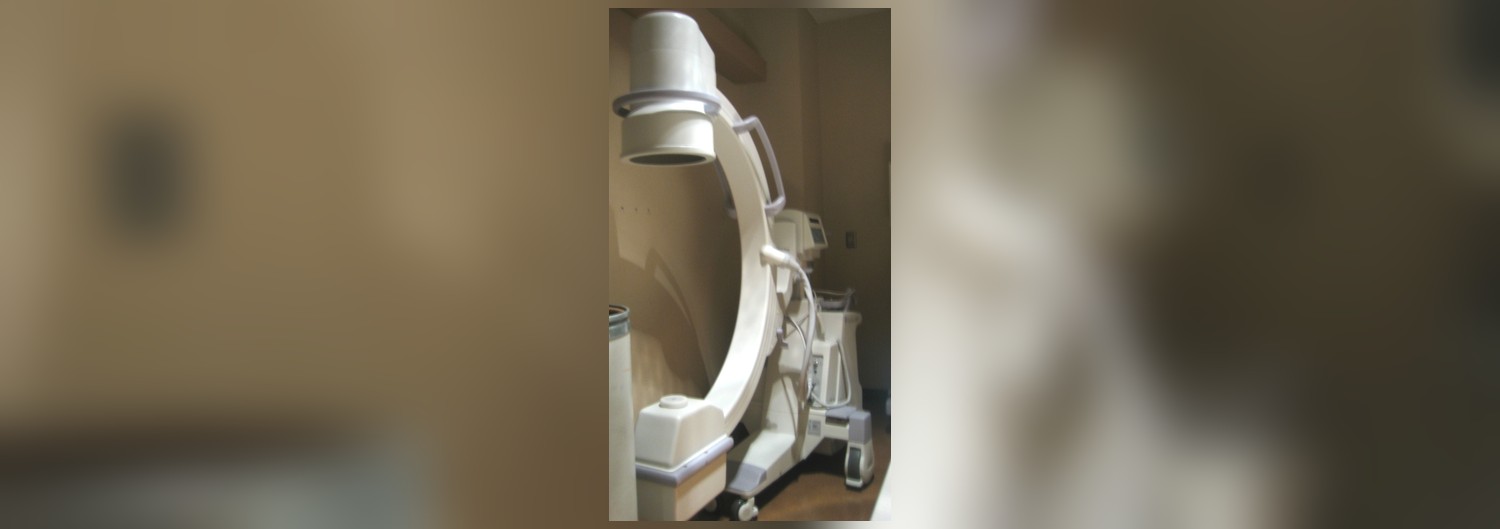
A portable C-arm is a wheeled fluoroscopy system that you position around the patient instead of positioning the patient inside a fixed imaging room. In practice the phrase covers two very different machines. The mini portable C-arm is built for hands, wrists, elbows, feet and ankles, and it is small enough to live in an ordinary procedure room. The full size portable C-arm images the whole body, and it is the size and weight of a piece of furniture. Both are sold as portable. Only one of them is portable in the sense a small practice means when it uses the word.
If you are weighing a portable C-arm for an office based practice, the decision is rarely about image quality. A portable C-arm decision is about anatomy, floor space, power, who is allowed to press the pedal, and what happens to your warranty the first time somebody wheels the unit out to a second office. This guide walks through the seven questions that actually decide the purchase, with the figures pulled from the manufacturer’s own operator manual rather than from a brochure.
What does a portable C-arm actually mean?
The regulator draws the line more clearly than the sales literature does. The US Food and Drug Administration classifies a C-arm fluoroscopic x-ray system under 21 CFR 892.1650 as an image intensified fluoroscopic x-ray system, Class II, product code RCC. Mini units carry their own product code, OXO, alongside RCC, so a mini portable C-arm is a distinct regulatory object rather than a marketing label. The distinction that matters clinically sits in the indications for use. In its clearance letter K183220 for a mini C-arm platform, the FDA describes the device as providing fluoroscopic visualization “when imaging limbs/extremities, shoulders; at locations including but not limited to, hospitals, ambulatory surgery, emergency, traumatology, orthopedic, critical care, or physician office environments.”

Read the OrthoScan Mobile DI operator manual and the same boundary is stated flatly. Its indications for use say the device generates, processes, captures, saves and transmits “fluoroscopic images of patient extremities,” and its equipment classification section says in one line: “This device is for examination of extremities only.” A mini portable C-arm is not a small general purpose fluoroscope. It is an extremity instrument, and if your procedure list includes spine or abdominal work, the category is settled before you compare any other spec.
How much does a portable C-arm really weigh, and what is it that moves?
Here is where most buying guides are misleading rather than wrong. The consensus description of a portable C-arm, repeated across vendor pages and equipment blogs, is a single wheeled unit that one staff member rolls from room to room. That picture is half right, and the half it leaves out is the half that governs where you can actually put the machine.
The OrthoScan Mobile DI operator manual, document 050-0014 Rev E, lists the imaging device itself at 16.8 kg, or 37 lb, standing 64.5 cm tall, 29 cm wide and 48.8 cm deep. That part of a portable C-arm is genuinely small. It is roughly the footprint of a filing cabinet drawer and one person can move it. The accessory cart that carries the monitor and the workstation is a separate object, and the manual lists it at 43.2 kg, or 96 lb, standing 171.5 cm tall, 61 cm wide and 67.3 cm deep. The external power supply adds another 2.7 kg.
So a mini portable C-arm is two pieces, and the piece that decides your room layout is the tall cart, not the imaging head. When you walk a room with a tape measure before you buy, measure for the cart. When you plan who moves the system between rooms, plan for somebody moving a 96 lb cart on castors and a 37 lb imaging device, not a single trolley.
The contrast with a full size unit is stark, and it is published. Ziehm Imaging’s technical specification sheet for the Ziehm Vision RFD, revision 05 dated December 2020, lists the C-arm mobile stand at 873 lb, or 396 kg, plus or minus 2 percent, with a separate monitor cart at 344 lb, or 156 kg. Both machines are sold as a portable C-arm. One of them is about a third of a ton before you add the monitors.
Will a portable C-arm fit the room you already have?
Floor space is only the first constraint. The geometry of a portable C-arm decides whether the anatomy you image will physically fit inside the machine. The Mobile DI manual gives the numbers directly: source to detector distance of 45 cm, source to skin distance of 10 cm, C-arm free space of 35 cm, and a depth of arc of 21.65 cm. Free space is the usable opening between the tube and the receptor. Thirty five centimetres is comfortable for a hand, a wrist, an elbow, a foot or an ankle on a small table. It is not a knee in a bulky immobiliser, and it is not a shoulder on a large patient.
Field of view is the other portable C-arm number to check against your procedures. The same manual lists operator selectable collimation of 15 cm by 12 cm in normal mode and 11 cm by 8 cm in magnification mode, on a CMOS flat detector running a 1.5k by 2k receptor. If you routinely need the whole forearm in one frame, measure a forearm and compare it to 15 cm before anybody quotes you a system.
One practical note that a spec sheet will not tell you. A portable C-arm needs clear floor on two sides of the procedure table, not one, because the arc has to swing. A room that comfortably holds a treatment chair and a stool will often hold the machine and leave nowhere to stand.
What does a portable C-arm need from the building?
This is the question that worries practice owners most and turns out to matter least. Many assume a fluoroscopy system means an electrical project. For a mini portable C-arm it usually does not. The Mobile DI manual states that the device “Operates on 100 VAC, 120 VAC, or 230 VAC power at 50Hz or 60Hz as indicated on the Power Supply Label,” that it “should only be plugged into a properly grounded three-way wire wall outlet,” and then, in the same passage, that “A special dedicated outlet is not required.” Its specification table lists current draw at 2.5 A or less at 120 volts, which is less than a household kettle.
The environmental limits are ordinary too. The manual gives an operating range of 15 to 32 degrees Celsius, which is 59 to 90 degrees Fahrenheit, at 20 to 80 percent relative humidity, non condensing. Storage tolerances are wider. And the machine is not slow to wake up: the startup procedure section notes that “After the power is turned on, the device will initialize in approximately 45 seconds.” That figure matters more than it looks. A system that takes several minutes to boot gets left switched on, and a system that gets left switched on changes how a practice thinks about its radiation safety policy.
Shielding, room registration and state radiation control requirements are a separate subject, and we cover them in detail in our guide to mini C-arm requirements for running fluoroscopy in a physician office, which also works through how mini and full size units compare on measured patient dose. Do not assume a smaller machine is automatically a lower dose machine. The published evidence is less tidy than the sales conversation.
Who will operate the portable C-arm, and how much training is that?
Staffing is usually the real constraint on whether a portable C-arm earns its place in the building. The manual is unambiguous about where responsibility sits: “It is the responsibility of the owner to ensure that the device is operated only by properly trained, qualified personnel who have obtained credentials from the appropriate authorities,” and the device is “intended for use on adult and adolescents by professional healthcare workers such as; doctors, surgeons and technologists.” The label also carries the standard federal caution restricting sale and use to a qualified practitioner.
The encouraging part is how modest the training burden is judged to be by the people who set the standard. The American Association of Physicists in Medicine, in Report No. 124 of December 2012, published a credentialing and privileging guide for users of fluoroscopic equipment. Its risk table places “Mini C-arms, Extremity Imaging” in the Low Risk category, the lowest of three tiers, with a recommended minimum of “Two hours didactic lecture and ‘hands-on’ demonstration, followed by practice, and competency examination.” Moderate risk procedures draw four hours in the same table and high risk procedures draw eight.
Two hours plus supervised practice is a realistic ask for a medical assistant or a radiologic technologist already on your payroll, which is why a portable C-arm rarely forces a new hire. State licensure rules still govern who may operate the beam where you practise, and those vary considerably, so confirm your own state’s rule before you build a schedule around one person. The FDA’s own fluoroscopy safety guidance puts the same duty on the practice, listing among facility responsibilities “Assuring that all operators of the system are trained and that they understand the operation of the fluoroscopic system, including the implications for radiation exposure from each mode of operation.”
What does portability cost you after the purchase?
This is the trap, and it is worth reading twice. The word portable implies you can take the machine wherever the work is. The warranty language on a portable C-arm frequently says otherwise.
OrthoScan’s published warranty, printed in the Mobile DI manual, warrants its products “to the original Buyer in the United States” and runs “for one year from the date of installation.” Its limitations section then states that the warranty “shall not apply to any Product that is: (a) repaired, moved to a different facility or location, or altered other than by OrthoScan, Inc. or its authorized service personnel.” Moving the unit between rooms inside one building is ordinary use. Moving it to a second office is, on the manufacturer’s own terms, a different thing entirely, and it is also normally a notification to your state radiation control program.
Two practices buy the same system for the same reason and get different answers here. A single site practice treats portability as room to room convenience and never touches the clause. A two site practice that planned to share one machine between locations discovers that the plan carries a warranty consequence and a regulatory step that nobody priced in. Ask the question before the quote, not after the install.
The second ongoing cost of a portable C-arm is the annual service cycle. The Mobile DI manual’s maintenance schedule requires yearly verification of radiation output and dose rate, kVp and tube current calibration, half value layer and primary barrier transmission, and a tube house radiation leak check. That is a physicist or an authorised service visit every year, and it belongs in your budget alongside the rest of your medical equipment maintenance planning.
How should a practice compare portable C-arm offers?
Once you know which portable C-arm category you need, comparing quotes is mostly about what is not on the price line. A useful checklist:
- Clearance record. Ask for the 510(k) number and look it up yourself. Every system on this market is FDA cleared rather than FDA approved, and the clearance is a specific, checkable document. Our FDA 510(k) device information page explains how that record works.
- Condition and what condition means. New, certified pre-owned and pre-owned units are all sold as a portable C-arm, and the warranty, the service history and the remaining life differ sharply between them.
- Delivery and installation. Confirm in writing whether freight, inside delivery and setup are included or quoted separately. On some platforms they are included and on others they are a line item.
- What ships with the system. Monitor cart, printer, image capture accessory and cabling are sometimes bundled and sometimes not.
- Who services it, and how fast. An extremity portable C-arm that is down for three weeks is a procedure schedule problem, not an equipment problem.
If adding imaging is part of a broader plan to keep work in the building, it is worth reading our overview of building ancillary services inside a medical practice alongside this one. The equipment decision is easier when the workflow question has already been answered.
Frequently Asked Questions
Is a mini C-arm the same thing as a portable C-arm?
A mini C-arm is one kind of portable C-arm. The portable C-arm category also includes full size mobile systems that image the whole body. The difference that matters is the indication: a mini unit is cleared for extremity imaging, and the OrthoScan Mobile DI manual states that the device is for examination of extremities only.
How much does a portable C-arm weigh?
A portable C-arm weight depends entirely on the category. The OrthoScan Mobile DI operator manual lists the mini imaging device at 16.8 kg, or 37 lb, with a separate accessory cart at 43.2 kg, or 96 lb. By comparison, Ziehm Imaging publishes a mobile stand weight of 873 lb, or 396 kg, for its full size Vision RFD, with a 344 lb monitor cart.
Does a portable C-arm need a dedicated electrical circuit?
Not on every platform. The OrthoScan Mobile DI manual states that the device should be plugged into a properly grounded three wire wall outlet and that a special dedicated outlet is not required, with current draw of 2.5 A or less at 120 volts. Confirm the requirement for the specific model you are quoted, because it is model specific.
How much training does a staff member need to operate a mini C-arm?
The American Association of Physicists in Medicine, in Report No. 124, classifies mini C-arm extremity imaging as low risk and recommends a minimum of two hours of didactic lecture and hands-on demonstration, followed by practice and a competency examination. State licensure rules on who may operate the beam still apply and vary by state.
Can I move a portable C-arm between two of my offices?
Physically a portable C-arm moves easily, but check the contract first. OrthoScan’s warranty terms, printed in the Mobile DI manual, exclude a product that has been moved to a different facility or location by anyone other than OrthoScan or its authorised service personnel. A move between facilities also normally triggers a notification to the state radiation control program.
Where HealthWright Technologies fits
HealthWright Technologies supplies mini and portable C-arm imaging systems to independent physician practices, alongside the diagnostic and therapeutic devices we have carried since 2000. You can see the platforms we supply on our mini C-arm imaging systems page, which lists the models available and how to request a quote. We sell to licensed healthcare practices, we do not fit or bill the studies, and pricing on this line is confirmed on a written quote rather than published.
If you want help working out whether a mini unit or a full size system fits your procedure list and your rooms, write to us at contact@healthwrighttechnologies.com or use the form on our contact page, and we will follow up. HealthWright Technologies, 60 Bear Creek Marina Rd, Mansfield, GA 30055.
Sources cited in this article: OrthoScan Mobile DI Operator’s Manual, document 050-0014 Rev E; American Association of Physicists in Medicine, Report No. 124, December 2012; Ziehm Imaging, Ziehm Vision RFD Technical Specifications, revision 05, December 2020; US Food and Drug Administration, product classification RCC under 21 CFR 892.1650, 510(k) K183220, and the FDA fluoroscopy safety guidance.
This article is general information for healthcare professionals and is not medical, legal, or billing advice. Consult your healthcare provider before starting any new treatment. Radiation safety, equipment registration, and operator licensure requirements vary by state; confirm your own state’s rules with your radiation control program.
Lead image: “Mobile X-ray machine” by Ben Stephenson via Wikimedia Commons, CC BY 2.0, cropped and placed on a blurred background.
Ready to see the CMAT Advantage in your practice?
Book a free 25-minute demo: see the full PAD + autonomic workup and how the three established CPT codes apply, with no obligation. Backed by our 60-day buyback guarantee.
Book a Free Demo →