
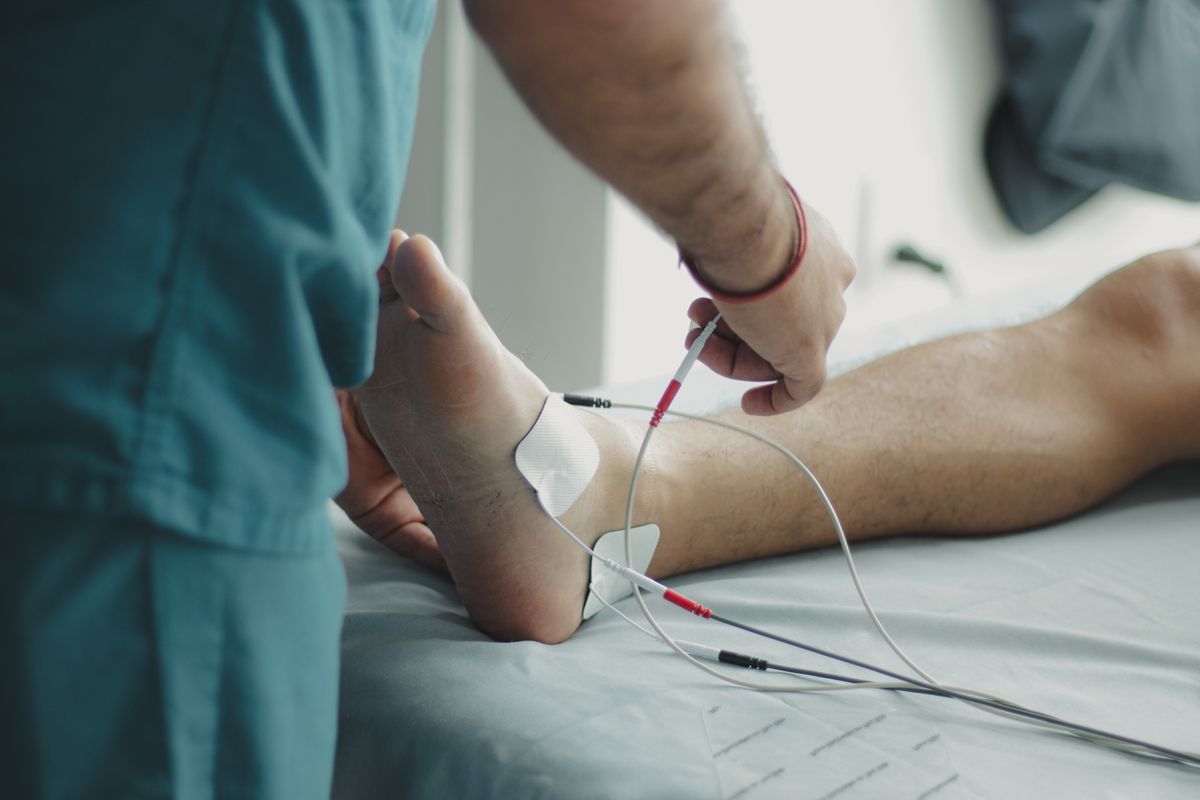
A diabetic foot exam is a structured clinical exam that checks the feet of patients with diabetes for signs of nerve damage and reduced circulation — the two changes that lead to ulcers and amputations. The American Diabetes Association recommends a comprehensive diabetic foot exam at least once a year for every patient with diabetes, and more often for higher-risk feet.
This guide breaks the diabetic foot exam into five essential steps an independent practice can complete in a single visit, and shows where objective vascular and autonomic testing closes the gap that a standard monofilament check leaves open.
How Do You Do a Diabetic Foot Check?
A diabetic foot check is done in one sitting, in this order: inspect the skin and the structure of the foot, test protective sensation with a 10-gram monofilament plus at least one additional sensory test, palpate the pedal pulses and add an ankle-brachial index when pulses are diminished or risk factors are present, add objective autonomic and small-fiber testing for patients with documented symptoms or risk indications, then assign an ADA foot-risk category and document the findings with the plan. The same visit is written up under several names. A diabetic foot assessment, a diabetic foot examination and a diabetic foot check all describe this exam, and the American Diabetes Association Standards of Care call it a comprehensive foot evaluation. The five steps below cover each component in full.
What Is a Diabetic Foot Exam and Why Does It Matter?
A diabetic foot exam is a focused physical and neurological assessment that checks for peripheral neuropathy, peripheral artery disease (PAD), skin breakdown, and structural deformity in patients with diabetes. The goal is simple: find the feet at risk.
The stakes are high. Diabetes is the leading cause of non-traumatic lower-limb amputation, and the large majority of those amputations are preceded by a foot ulcer that began as an unnoticed injury on an insensate foot.
Identifying loss of sensation and poor circulation lets clinicians intervene with footwear, education, glycemic management, and closer follow-up — steps that may help reduce the risk of ulceration and amputation. According to the American Diabetes Association Standards of Care, every patient with diabetes should receive a comprehensive foot evaluation at least annually, while patients with sensory loss, prior ulceration, or amputation should have their feet inspected at every visit.

What Are the 5 Essential Steps of a Complete Diabetic Foot Exam?
A complete diabetic foot exam combines a careful hands-on assessment with objective measurement. These five steps cover everything the ADA Standards of Care expect a thorough exam to include.
- Visual skin and structural inspection. Examine the skin for breakdown, calluses, fissures, and color changes; check between the toes and around the nails; and note structural deformities such as bunions, hammertoes, and prominent metatarsal heads that raise plantar pressure and ulcer risk.
- Loss of protective sensation (LOPS) testing. Use the 10-gram Semmes-Weinstein monofilament at the standard plantar sites, paired with at least one additional test — vibration with a 128-Hz tuning fork or a vibration perception threshold device, pinprick, temperature, or ankle reflexes. The Ipswich touch test is a validated alternative when a monofilament is unavailable.
- Vascular assessment. Palpate the dorsalis pedis and posterior tibial pulses and ask about claudication, rest pain, or slow-healing wounds, and add an ankle-brachial index when pulses are diminished or risk factors are present. PAD is one of the two findings that move a patient up the ADA foot-risk scale.
- Autonomic and small-fiber testing. This is the objective layer most routine exams skip. Sudomotor testing and heart-rate-variability analysis document and characterize autonomic and small-fiber dysfunction in patients with documented symptoms or signs, and the results inform management.
- Risk stratification and documentation. Assign an ADA foot-risk category, set the appropriate follow-up interval, and document every finding with the clinical plan. Clear documentation supports continuity of care and clean claims.
How Often Should Patients Have a Diabetic Foot Exam?
Every patient with diabetes should have a comprehensive diabetic foot exam at least once a year. Frequency increases with risk: patients with loss of protective sensation, diagnosed PAD, foot deformity, or a history of ulceration or amputation warrant more frequent evaluation, and the ADA advises inspecting the feet of the highest-risk patients at every clinical visit.
Building a recall workflow around these intervals — and flagging high-risk patients in the EHR — helps a practice stay consistent and audit-ready.
What Are the Diabetic Foot Risk Categories?
After the exam, each patient is placed in a risk category that sets how often the feet should be rechecked. The widely used International Working Group on the Diabetic Foot (IWGDF) system — reflected in the ADA Standards of Care — stratifies risk from very low to high based on loss of protective sensation (LOPS), peripheral artery disease (PAD), foot deformity, and any history of ulceration or amputation. The higher the category, the shorter the recommended exam interval.
| Category | Ulcer Risk | Characteristics | Recommended Exam Frequency |
| 0 | Very low | No LOPS and no signs of PAD | Once a year |
| 1 | Low | LOPS or PAD | Once every 6–12 months |
| 2 | Moderate | LOPS + PAD, or LOPS + foot deformity, or PAD + foot deformity | Once every 3–6 months |
| 3 | High | LOPS or PAD, plus a history of foot ulcer, lower-extremity amputation, or end-stage renal disease | Once every 1–3 months |
Accurate stratification depends on reliably detecting LOPS and PAD — the two findings that move a patient up the scale. This is where objective measurement helps: in symptomatic patients, adding ankle-brachial index and autonomic data to the diabetic foot exam reduces the chance that a patient is under-classified on the hands-on exam alone.
What a Standard Diabetic Foot Exam Does Not Measure
The monofilament test is the workhorse of the diabetic foot exam, but it measures loss of protective sensation, a large-fiber finding.
Sudomotor testing measures small unmyelinated nerve fibers. Sudomotor (sweat-gland) dysfunction is a recognized feature of diabetic autonomic and small-fiber neuropathy, and testing documents and characterizes it in patients with documented symptoms or signs so results inform management.
Research summarized in Frontiers in Neurology discusses quantitative sudomotor testing for distal symmetric polyneuropathy and small-fiber neuropathy, while intraepidermal nerve fiber density remains the reference standard. In patients with documented symptoms or signs, objective autonomic and vascular measurement adds structured data to the diabetic foot exam that informs management.
How the CMAT Advantage Supports the Diabetic Foot Exam
The CMAT Advantage™ from HealthWright Technologies is a diagnostic platform built on FDA-cleared component devices that adds the objective, measurable layers of the diabetic foot exam in a single 7-to-10-minute test. It captures the ankle-brachial index for vascular assessment alongside heart-rate-variability and sudomotor measurements for autonomic and small-fiber function, objective measurements that a monofilament alone cannot provide. The system generates standardized, color-coded reports for the chart and complements, rather than replaces, the clinician’s hands-on inspection and judgment.
Because the vascular and autonomic components map to long-established procedure codes, a structured exam with documented indications can map to established CPT codes — for example, ABI testing plus autonomic function testing. Coverage and correct coding vary by payer and remain the responsibility of the practice and its billing team.
For independent practices that already evaluate patients for diabetic neuropathy, layering objective autonomic and vascular data into the diabetic foot exam, when symptoms or signs are documented, strengthens both clinical insight and the practice’s standard of care. To see how it fits an existing workflow, explore the HealthWright partnership program.
Who Should Be Prioritized for Vascular and Autonomic Testing?
Not every encounter needs the full objective workup, but several groups benefit most from adding ABI and autonomic testing to the diabetic foot exam. Professional guidelines from the American College of Cardiology and American Heart Association support ankle-brachial index testing for the following adults:
- adults aged 65 and older
- adults 50 and older who have atherosclerosis risk factors or a family history of PAD
- adults younger than 50 who have diabetes plus at least one additional risk factor such as smoking, hypertension, or high cholesterol
Within a diabetes population, the highest-yield candidates for objective autonomic and vascular testing include patients with long-standing diabetes, suboptimal glycemic control, established cardiovascular disease, or symptoms such as burning feet, numbness, exertional leg pain, or slow-healing wounds.
Prioritizing these patients keeps a testing program focused and clinically meaningful, anchored to documented indications. Capturing objective baselines also makes year-over-year comparison possible, which informs management at follow-up visits.
Diabetic Foot Exam: What Each Component Detects
| Exam Component | What It Checks For | Measurement Type | Typical Tool |
| Skin & structural inspection | Calluses, deformity, breakdown, ulcer risk | Visual inspection | Visual exam |
| 10-g monofilament (LOPS) | Loss of protective sensation | Bedside sensory test | Monofilament + 1 added test |
| Pedal pulses & ABI | Peripheral artery disease, perfusion | Manual and objective | Palpation / ABI (CMAT) |
| Sudomotor & HRV | Small-fiber & autonomic dysfunction | Objective, quantitative | Autonomic testing (CMAT) |
Frequently Asked Questions About the Diabetic Foot Exam
What is included in a diabetic foot exam?
A complete diabetic foot exam includes a visual skin and structural inspection, testing for loss of protective sensation with a 10-gram monofilament plus at least one additional sensory test, a vascular assessment of the pedal pulses (and an ankle-brachial index when indicated), and objective autonomic and small-fiber testing when indicated, followed by risk stratification and documentation.
How often should a diabetic foot exam be done?
The American Diabetes Association recommends a comprehensive diabetic foot exam at least once a year for every patient with diabetes. Patients with loss of protective sensation, peripheral artery disease, foot deformity, or a prior ulcer or amputation should be examined more frequently — often at every visit.
What does a diabetic foot exam miss about small-fiber and autonomic nerve function?
Objective autonomic and small-fiber testing, such as sudomotor and heart-rate-variability testing, documents small-fiber and autonomic dysfunction that a monofilament test does not capture. Testing is ordered on the basis of documented symptoms or signs, and the result informs clinical management.
What ABI value indicates peripheral artery disease?
An ankle-brachial index of 0.90 or lower is generally considered diagnostic of peripheral artery disease. Values between 1.00 and 1.40 are typically normal and 0.91 to 0.99 is borderline, while values above 1.40 suggest non-compressible, calcified arteries and may require additional testing such as a toe-brachial index.
How is diabetic foot ulcer risk classified?
The IWGDF system used in the ADA Standards of Care sorts patients into four categories: very low (no loss of protective sensation and no PAD, examined yearly), low (LOPS or PAD, every 6–12 months), moderate (two of LOPS, PAD, or foot deformity, every 3–6 months), and high (LOPS or PAD plus a prior ulcer, amputation, or end-stage renal disease, every 1–3 months). The category determines how often the diabetic foot exam should be repeated.
Is a diabetic foot assessment the same as a diabetic foot exam?
Yes. Diabetic foot assessment, diabetic foot examination, diabetic foot check and comprehensive foot evaluation all describe the same visit: a structured look at the skin and structure of the foot, sensory testing for loss of protective sensation, a vascular check of the pedal pulses, and risk stratification with documentation. The American Diabetes Association Standards of Care use the term comprehensive foot evaluation. Practices pick the wording that matches their own templates, and the components are the same either way.
Conclusion
A thorough diabetic foot exam protects patients from the diabetes complications that are most manageable when identified through the structured exam. The five-step workflow — inspection, sensation testing, vascular assessment, autonomic and small-fiber testing, and risk stratification — gives independent practices a repeatable standard, and objective vascular and autonomic measurement adds structured data when symptoms or signs are documented.
To learn how the CMAT Advantage can add objective ABI and autonomic testing to your diabetic foot exam workflow, contact HealthWright Technologies at (678) 322-7146 or email contact@healthwrighttechnologies.com.
This article is for educational purposes for healthcare professionals and does not constitute medical or billing advice. Patients should consult their healthcare provider about their individual care. CPT codes are referenced for general information only; CPT® is a registered trademark of the American Medical Association, and code applicability, coverage, and reimbursement should be verified with each payer.
References
- Retinopathy, Neuropathy, and Foot Care: Standards of Care in Diabetes — American Diabetes Association
- Peripheral Artery Disease: Screening With the Ankle-Brachial Index — U.S. Preventive Services Task Force
- Sudomotor Testing of Diabetes Polyneuropathy — Frontiers in Neurology
- IWGDF Practical Guidelines on the Prevention and Management of Diabetes-Related Foot Disease (2023) — International Working Group on the Diabetic Foot
Related Articles
- TM-Flow System and Diabetic Neuropathy: Objective Testing
- Understanding Sudomotor Testing: A Comprehensive Guide
- Coding the CMAT Encounter: 3 CPT Codes From One Multi-System Test
Ready to see the CMAT Advantage in your practice?
Book a free 25-minute demo: see the full PAD + autonomic workup and how the three established CPT codes apply, with no obligation. Backed by our 60-day buyback guarantee.
Book a Free Demo →


